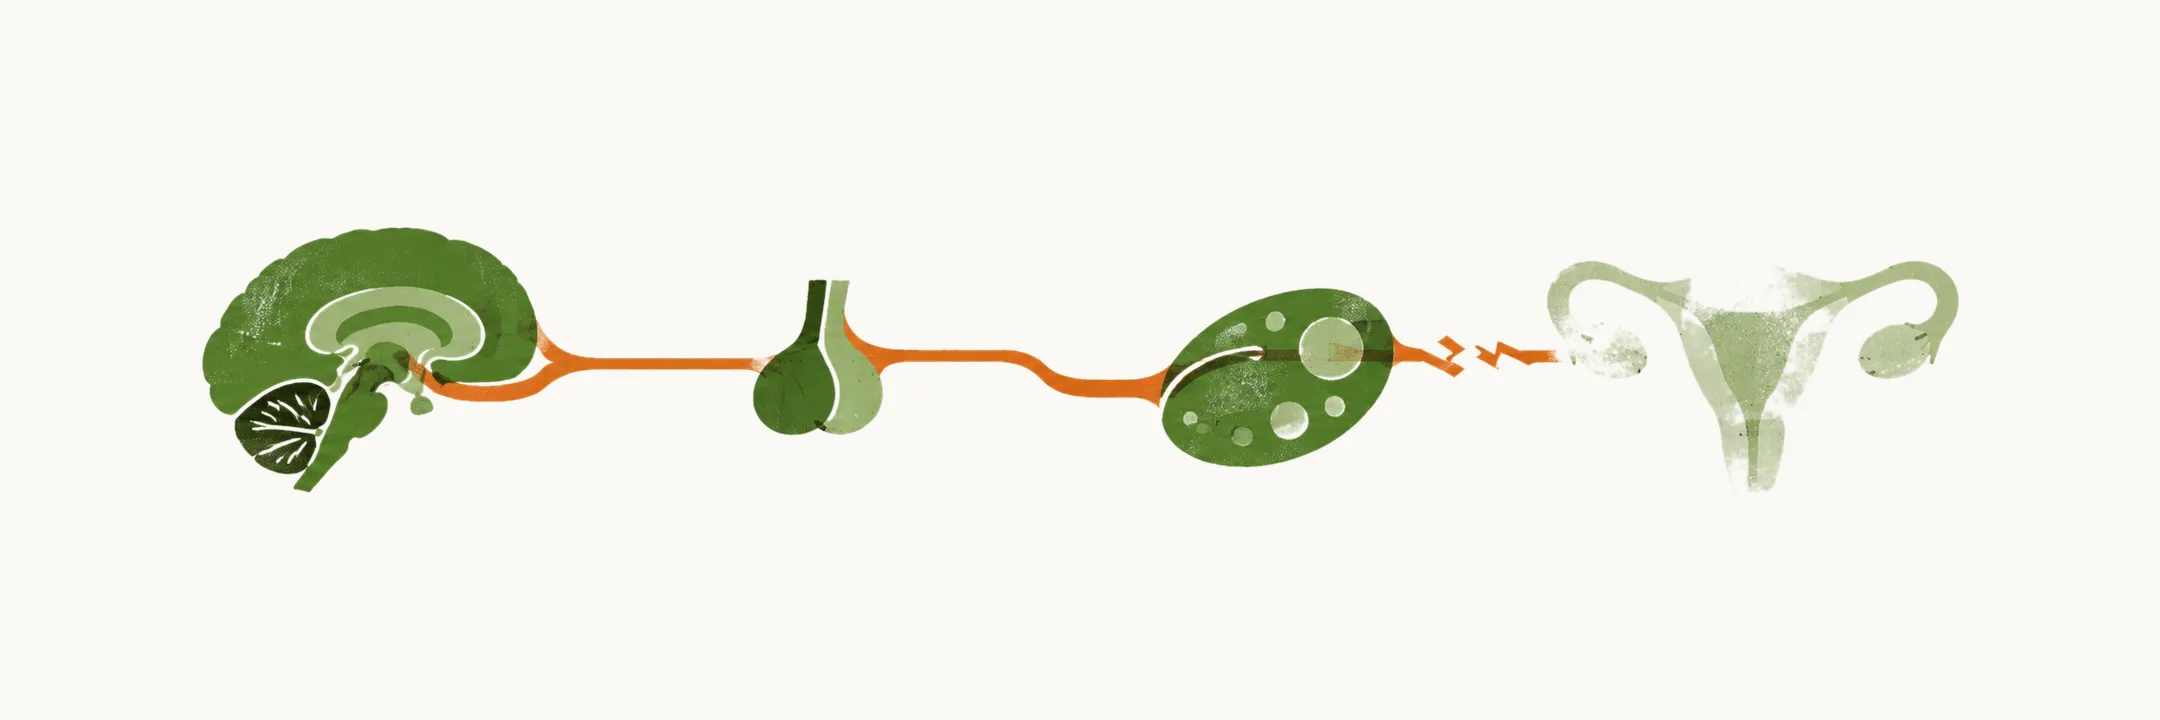
Menstrual cycles occur at intervals of 28±3 days in two thirds of women, with a normal range of 21–35 days. Amenorrhea is the absence of menstruation during the reproductive years when it is not caused by pregnancy, lactation or menopause, and it is a sign rather than a diagnosis: it points to a disorder somewhere in the hypothalamus–pituitary–ovary–uterus axis, the four components that must all function for menstruation to occur.
Amenorrhea may be defined either way:
- lack of menses for 3 consecutive months with a past history of menstruation (secondary amenorrhea);
- absence of menarche in a girl after the age of 15 years (primary amenorrhea).
Because amenorrhea is only a sign, the cause can lie at any point in the axis, and treatment follows the cause rather than the amenorrhea itself.
Choose a route through the topic
The first question is therefore where in the axis the fault lies. If the approach to a patient with amenorrhea is unfamiliar, start with the causes and the initial evaluation, which sort a patient into a category; the specific entity and its management follow from them.
- Causes and Initial Evaluation of Amenorrhea: how amenorrhea is classified by cause into anatomical amenorrhea, ovarian failure and chronic anovulation, and how a patient with amenorrhea is evaluated, from the four aspects of history and physical examination to the exclusion of pregnancy and the first-line laboratory tests.
- Hypergonadotropic Amenorrhea: amenorrhea with a high gonadotropin level (gonadotropins are the pituitary hormones FSH and LH, which drive the ovary), most often caused by primary ovarian insufficiency, with the terminology of gonadal dysgenesis and the genetic, autoimmune and environmental causes behind it.
- Management of Amenorrhea: how each category is treated, from restoring energy balance in to hormone replacement in ovarian failure.