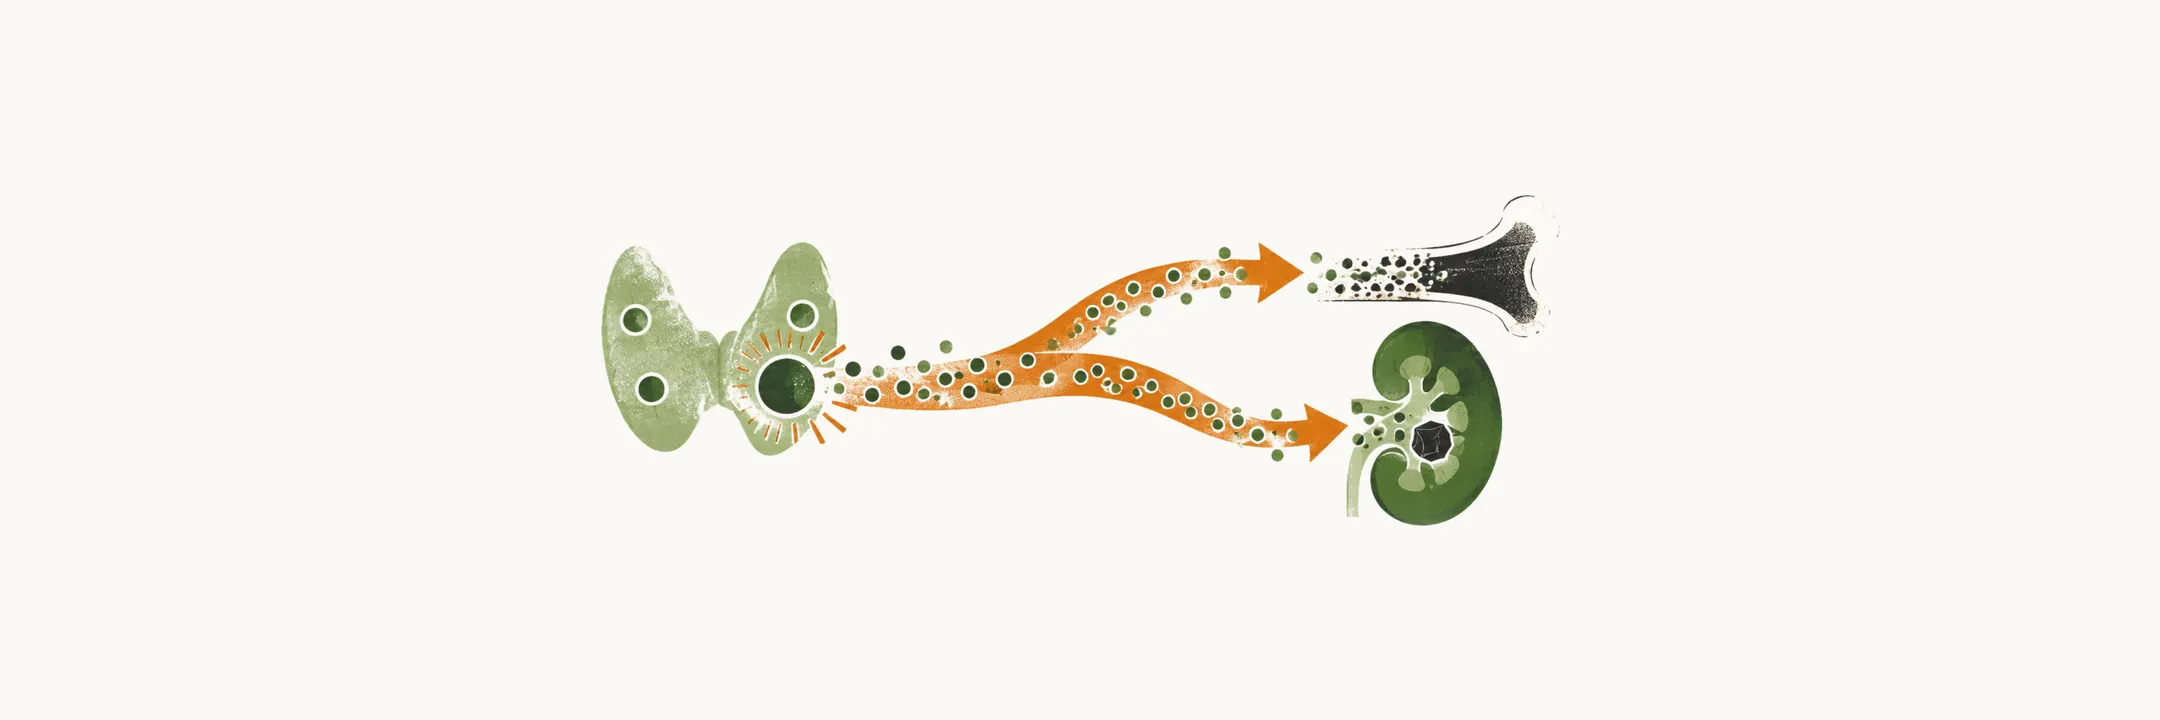
Primary hyperparathyroidism (PHPT) means that one or more parathyroid glands make too much parathyroid hormone (PTH). It is characterised by an elevated calcium concentration in the blood with a concomitant elevated or inappropriately normal PTH level, and it is one of the most common causes of hypercalcemia. Because calcium and PTH act on many tissues, the effects of PHPT are spread across the organ systems, from the skeleton and kidneys to the cardiovascular, nervous, and gastrointestinal systems.
A reader new to the topic can start with the first satellite, which explains where the glands sit, who develops PHPT and how the over-production arises, and then move to the clinical picture and the bone disease before the diagnostic and management material.
- Epidemiology and pathogenesis of primary hyperparathyroidism — where the parathyroid glands sit, who develops PHPT, and how over-production of PTH from one or more glands arises.
- Clinical presentation of primary hyperparathyroidism — how PHPT shows itself across organ systems, from the kidney and the heart to the nervous system and the gut.
- Bone disease in primary hyperparathyroidism — the skeletal changes, the cortical-predominant loss of bone, and the imaging that explains why fractures are site-specific.
- Unusual forms of primary hyperparathyroidism — the neonatal forms linked to CaSR mutations, PHPT in pregnancy, acute parathyroid crisis, parathyroid carcinoma, and parathyromatosis.
- Diagnosis and treatment of primary hyperparathyroidism — the biochemical grounds for diagnosis, the differential diagnosis, the workup, and the criteria that make surgery first-line.