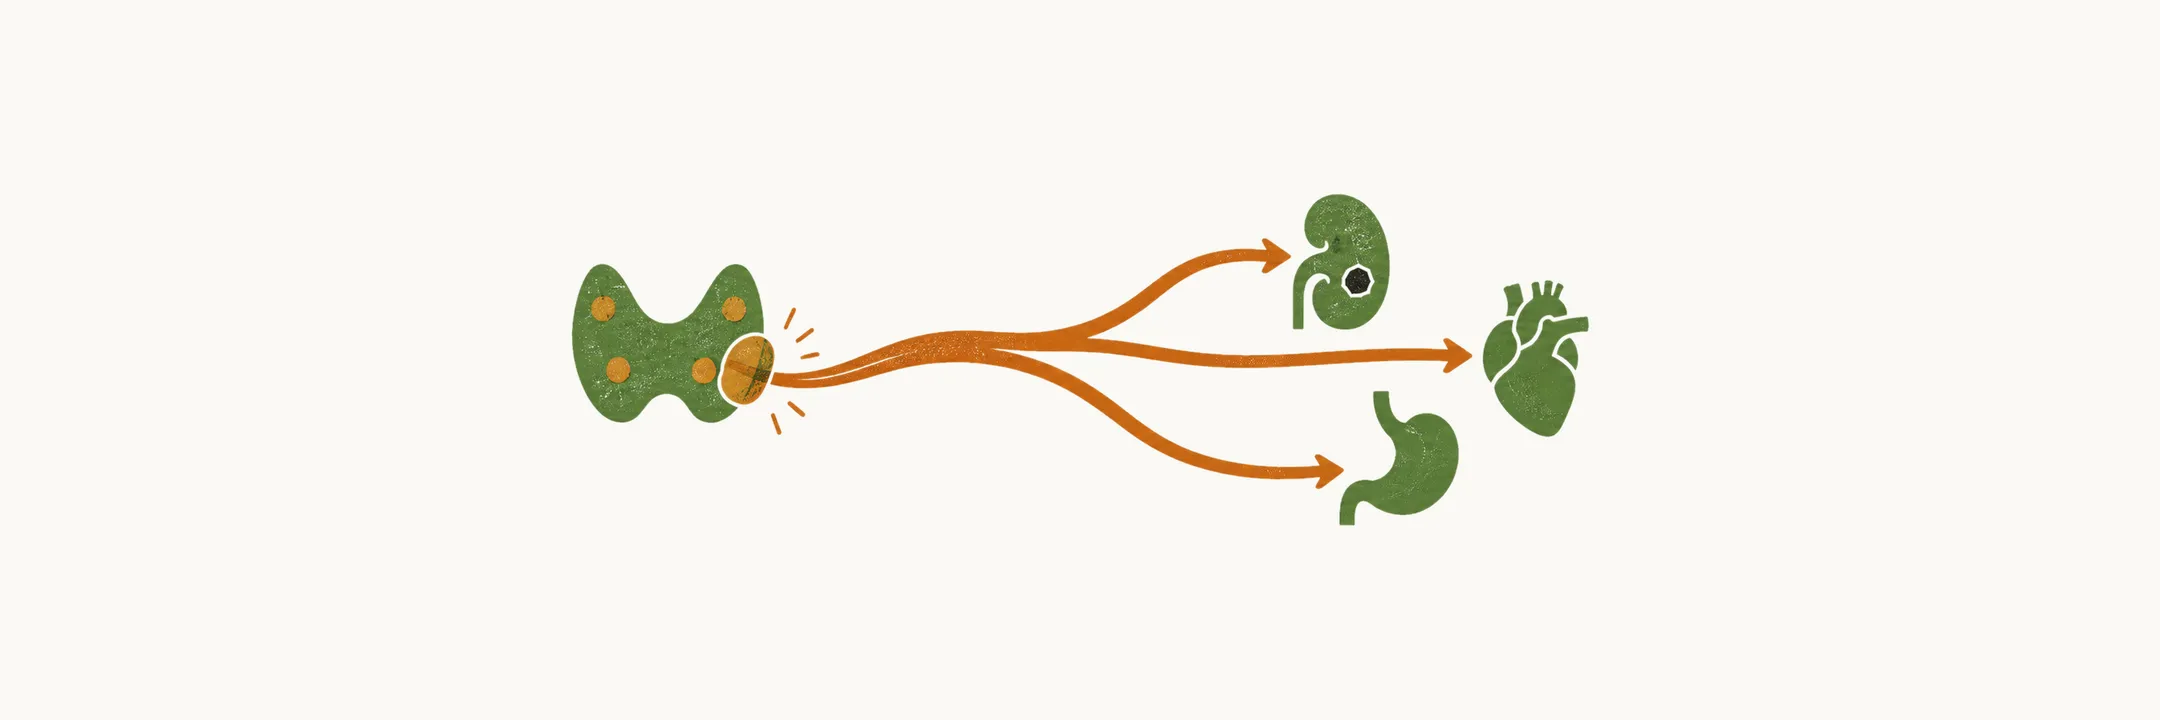
Primary hyperparathyroidism (PHPT) affects several organ systems, and the picture has shifted from the severe disease seen in the past towards an incidentally detected, often asymptomatic one. Most cases are nowadays diagnosed incidentally in the early stages, thanks to screening of calcium in the blood. The features that can still be seen are described below, starting with the kidney, where calcium handling produces the most classic finding.
Nephrolithiasis and renal function
PTH enhances calcium reabsorption in the kidney, but classically in patients with PHPT there is hypercalciuria (a high level of calcium in the urine) and nephrolithiasis (kidney stones). This paradox is due to the amount of calcium that is filtered being much higher than the reserve for calcium reabsorption.
In patients with PHPT there is higher production of vitamin D in the form of calcitriol, which increases the intestinal calcium absorption, and the level of calcium in the urine is correlated with the level of vitamin D. Beyond the vitamin D level, which is the main risk factor for hypercalciuria and nephrolithiasis in PHPT patients, younger age and male sex are other important risk factors for kidney involvement in these patients.
Estimated symptomatic nephrolithiasis occurs in about 15-20% of the cases, but screening of patients who are asymptomatic for nephrolithiasis shows a higher prevalence of kidney stones, in an asymptomatic form.
Cardiovascular system
Hypercalcemia is associated with hypertension, coronary artery disease, valve calcification, left ventricular hypertrophy, hypercontractility, and arrhythmia. In PHPT, hypertension is especially common when the disease is associated with the MEN syndromes, and both the hypercalcemia and the high level of PTH hormone are shown to be associated with a higher rate of coronary artery disease. Valve calcification happens mostly in severe PHPT.
The degree of disease matters for the outcome: patients who are asymptomatic for PHPT have very low cardiovascular-related mortality, in comparison to symptomatic patients, who have a higher rate of cardiovascular disease.
Neurological, psychological, and cognitive features
The most common neuropsychological complaints of PHPT are easy fatiguability and weakness. The classical form of PHPT was associated with a neurological syndrome characterised by easy fatiguability, symmetric proximal muscle weakness, and type II muscle atrophy.
Mild PHPT, with a calcium level less than 12 mg/dl, has been suggested to be associated with depression, anxiety, fatigue, sleep disturbances, and decreased quality of life.
Memory decline and impairment of other aspects of cognition have been reported less commonly. This decline of cognition has been hypothesized to be associated with cerebrovascular dysfunction caused by the hypercalcemia.
Gastrointestinal system
Peptic ulcer disease (ulceration of the stomach or duodenum) is common in 10% of the patients with PHPT, and in PHPT associated with the MEN1 syndrome that incidence is as high as 40%, due to the Zollinger-Ellison syndrome and gastrinoma.
Pancreatitis is the other gastrointestinal condition linked to hypercalcemia. Although hypercalcemia can underlie pancreatitis, most studies show that pancreatitis is not increased in mild PHPT with a calcium level less than 12 mg/dl.
Disorders associated with PHPT
Epidemiologically, though not etiologically, some disorders are related to PHPT: hypertension, gout, and pseudo-gout.
Skeletal system
The skeleton is a principal target of PHPT. The classic radiographic signs are now rare, but most patients still have subclinical bone involvement. The pattern of that loss, and the markers and imaging that measure it, are the subject of Bone disease in primary hyperparathyroidism.