Most children with acute gastroenteritis recover within a few days without treatment beyond oral fluids, the organism is cleared on its own within days or weeks, and complications are uncommon. They matter out of proportion to their frequency because preventing them is what most of the management of gastroenteritis is for. They are worth sorting by cause: those that follow the loss of fluid and the fall in intake, those produced by the organism itself, and those produced by the treatment.
The usual course
The shape of an uncomplicated episode is predictable. Diarrhea lasts 5 to 7 days and in most children stops within 2 weeks; vomiting lasts 1 to 2 days and in most stops within 3 days.
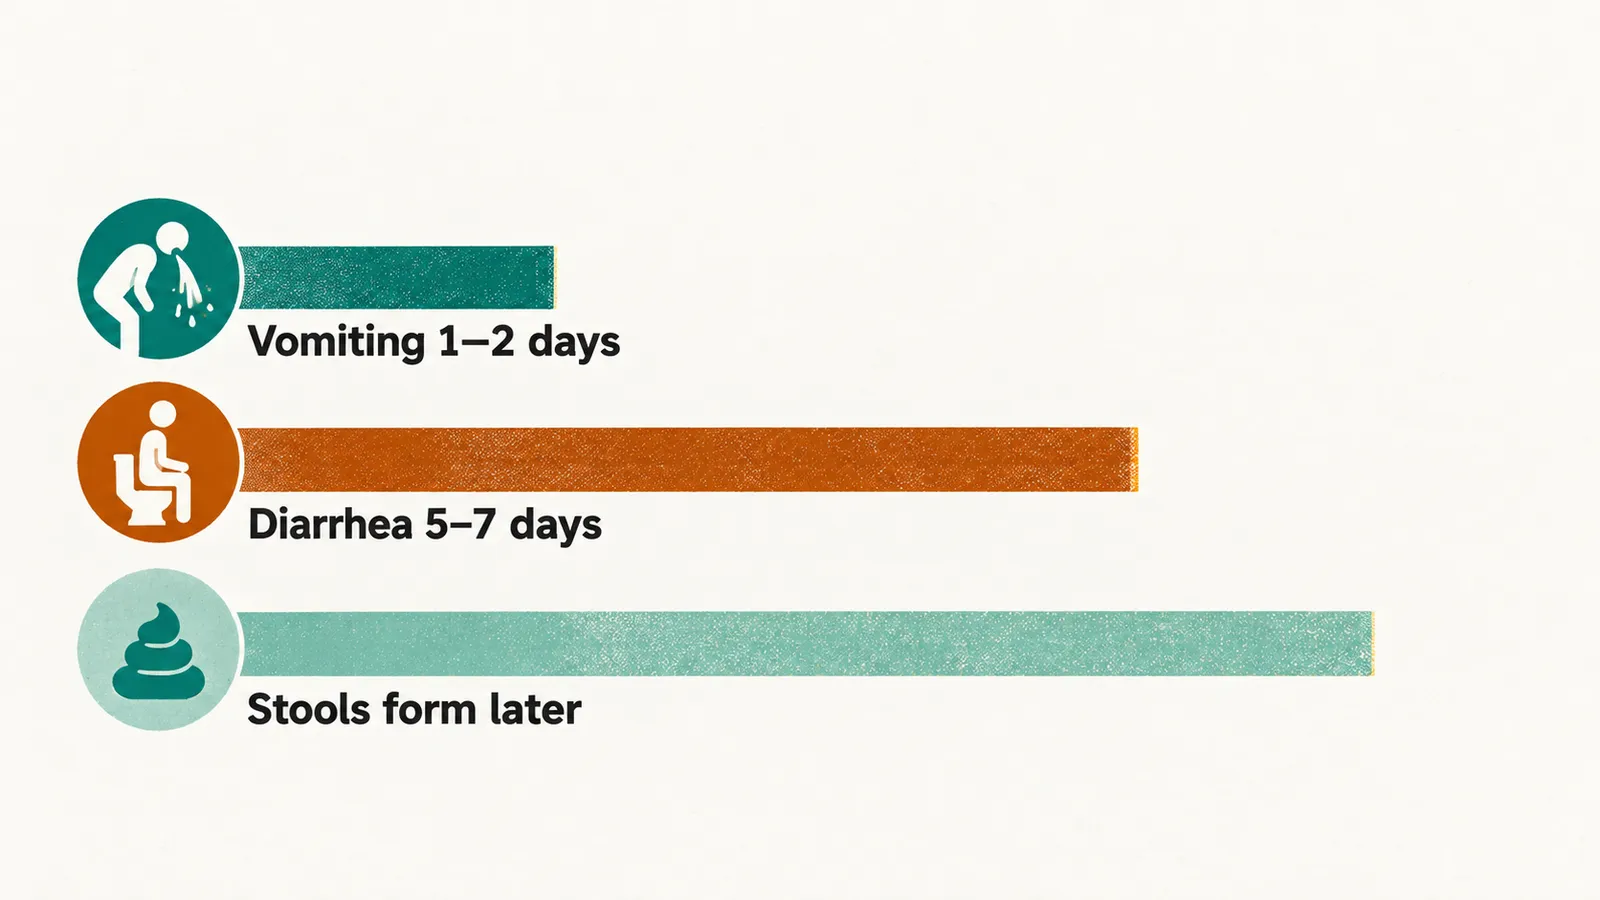
Recovery does not coincide with discharge, either from hospital or from the acute illness: stools take some days to become formed again, and a child may need a few days at home before returning to normal social life. Sufficient rehydration — drinking, passing urine, gaining weight — is what ends hospital treatment, even if the stools are still loose.
That account holds in Europe, where death from gastroenteritis is rare. Worldwide the picture differs: diarrheal disease is the third leading cause of death in children aged 1 to 59 months, with around 443,832 deaths in children under 5 each year, and malnutrition both raises the risk of a severe episode and worsens with each one.
Problems that settle by themselves
Not everything that follows an episode needs treatment beyond time. Secondary lactase deficiency is the clearest example: the osmotic diarrhea it adds settles as the mucosa regenerates and brush-border enzyme activity returns, so it is a temporary consequence of the illness rather than a new diagnosis to pursue. What to feed in the meantime, and when a lactose-free feed is worth using, are decided in Refeeding and Drug Therapy in Acute Diarrhea. At the milder end of the same scale, appetite and stool consistency take a few days to return to normal after the acute illness has settled.
Complications of fluid loss and poor intake
Shock and the kidney
Dehydration that is not replaced ends in hypovolemic shock, and shock that is not corrected ends in death. The recognition of shock and the bolus that treats it are in Admission and Shock Management in Acute Diarrhea.
The kidney is among the first organs to suffer when circulating volume falls. In an analysis of a United States inpatient database covering children hospitalized with diarrheal illness, acute kidney injury — a sudden fall in kidney function — was recorded in 0.8% of the admissions, and those children had about eight times the odds of dying and roughly 3 more days in hospital than children without it.
When dehydration is the cause, the injury reflects reduced perfusion rather than damage by the organism, so replacing volume is also the treatment. Urine output and kidney function belong in the monitoring of any child who stays dehydrated or hypotensive, and an injury that has progressed further before volume is restored recovers less reliably.
Hypoglycemia
Young children have limited glycogen reserves and usually stop eating when they vomit, so blood glucose can fall during an episode. Rotavirus gastroenteritis in particular is associated with a higher risk of metabolic disturbance, and hypoglycemia is the disturbance most often seen. The picture is easily missed, because drowsiness and lethargy are also signs of dehydration, and ketotic hypoglycemia — a low glucose with ketones after a period of vomiting and poor intake — is more common in younger children.
Two consequences follow. Blood glucose belongs in the assessment of a child who is drowsy, unable to keep fluids down or starting intravenous fluids, and it is measured with the electrolytes in that situation (see Investigations in Acute Diarrhea and Dehydration). Once fluid volume has been restored, the maintenance solution contains dextrose partly for this reason: glucose supports brain metabolism and reduces protein catabolism and sodium loss.
A complication of the organism: hemolytic uremic syndrome
Hemolytic uremic syndrome (HUS) is a thrombotic microangiopathy — the combination of red cells destroyed as they pass through damaged small vessels, a low platelet count and acute kidney injury — and it is the most common cause of acute kidney injury in children. It is rare, and it is the complication that changes how a bloody diarrhea is handled.
HUS is caused by Shiga toxin-producing E. coli (STEC) in about 8 in 10 children who develop it, and roughly 8% of people diagnosed with STEC infection of the O157 serotype, the most common one, go on to develop HUS. Both the infection and the risk of HUS are highest in children under 5 years. Bloody diarrhea with low or no fever is the typical presentation of these organisms, and antibiotics are withheld in that situation because the evidence on whether they change the risk of HUS is conflicting; the reasoning is in Refeeding and Drug Therapy in Acute Diarrhea. A child with confirmed STEC infection is monitored for the features of HUS rather than treated empirically.
Seizures during the illness
A convulsion during acute gastroenteritis has several possible explanations, drawn from more than one of these groups, and they are not all benign. The recognised benign pattern is the afebrile seizure of viral gastroenteritis: brief and generalised, in a child with a mild illness and no severe dehydration or electrolyte disturbance, and associated mainly with rotavirus and norovirus.
A seizure is read differently in a child who looks toxic, or in one who convulses at presentation rather than during recovery. In a retrospective controlled study of nontyphoid Salmonella gastroenteritis, children who appeared toxic or had a seizure at admission were more likely to have bacteremia — bacteria in the bloodstream — than children with isolated gastrointestinal symptoms. Severe hypernatremia and hyponatremia are the third explanation, and the sodium measurement is what separates them; the clinical features that suggest hypernatremia are in Clinical Assessment of Acute Diarrhea and Dehydration.
Harm from treatment
Two complications come from treatment rather than from the illness, and both are avoidable when the rules for fluid composition and for the rate of sodium correction are followed. Fluid more dilute than plasma can cause acute hyponatremia, including in children who were normonatremic when treatment started. Correcting hypernatremic dehydration faster than the brain can adapt shifts water into brain cells and can produce cerebral edema, because a brain exposed to sustained hypernatremia has adjusted its own osmolality and needs time to readjust. The recognition of the sodium abnormality is part of Clinical Assessment of Acute Diarrhea and Dehydration, and the composition of the fluid and the rate at which sodium may safely fall belong to Rehydration Management in Acute Diarrhea.
At a glance
- The usual outcome is full recovery in a few days, with diarrhea lasting 5 to 7 days and vomiting 1 to 2 days; discharge comes before the stools are back to normal.
- The deficit, not the organism, causes most of the harm in Europe: hypovolemic shock and acute kidney injury follow losses that outrun replacement.
- Acute kidney injury is uncommon but consequential — recorded in 0.8% of children hospitalized with diarrheal illness in a United States inpatient database, with about eight times the odds of dying and around 3 more days in hospital.
- Hypoglycemia is easily mistaken for dehydration and is common enough to justify a glucose measurement in a drowsy child or one starting intravenous fluids.
- Hemolytic uremic syndrome follows about 8% of diagnosed STEC O157 infections and is the most common cause of acute kidney injury in children, which is why antibiotics are withheld in bloody diarrhea with little or no fever.
- Seizures are usually benign afebrile convulsions of viral gastroenteritis, but a toxic-looking child or a seizure at presentation raises the possibility of bacteremia, and electrolytes are the other explanation to exclude.
- Two harms are iatrogenic: acute hyponatremia from unnecessarily dilute fluid, and cerebral edema from correcting hypernatremia too quickly.
Two things set most of this harm in motion — the infection itself, and a fluid loss that outruns replacement — and both can be reduced before a clinician is involved.