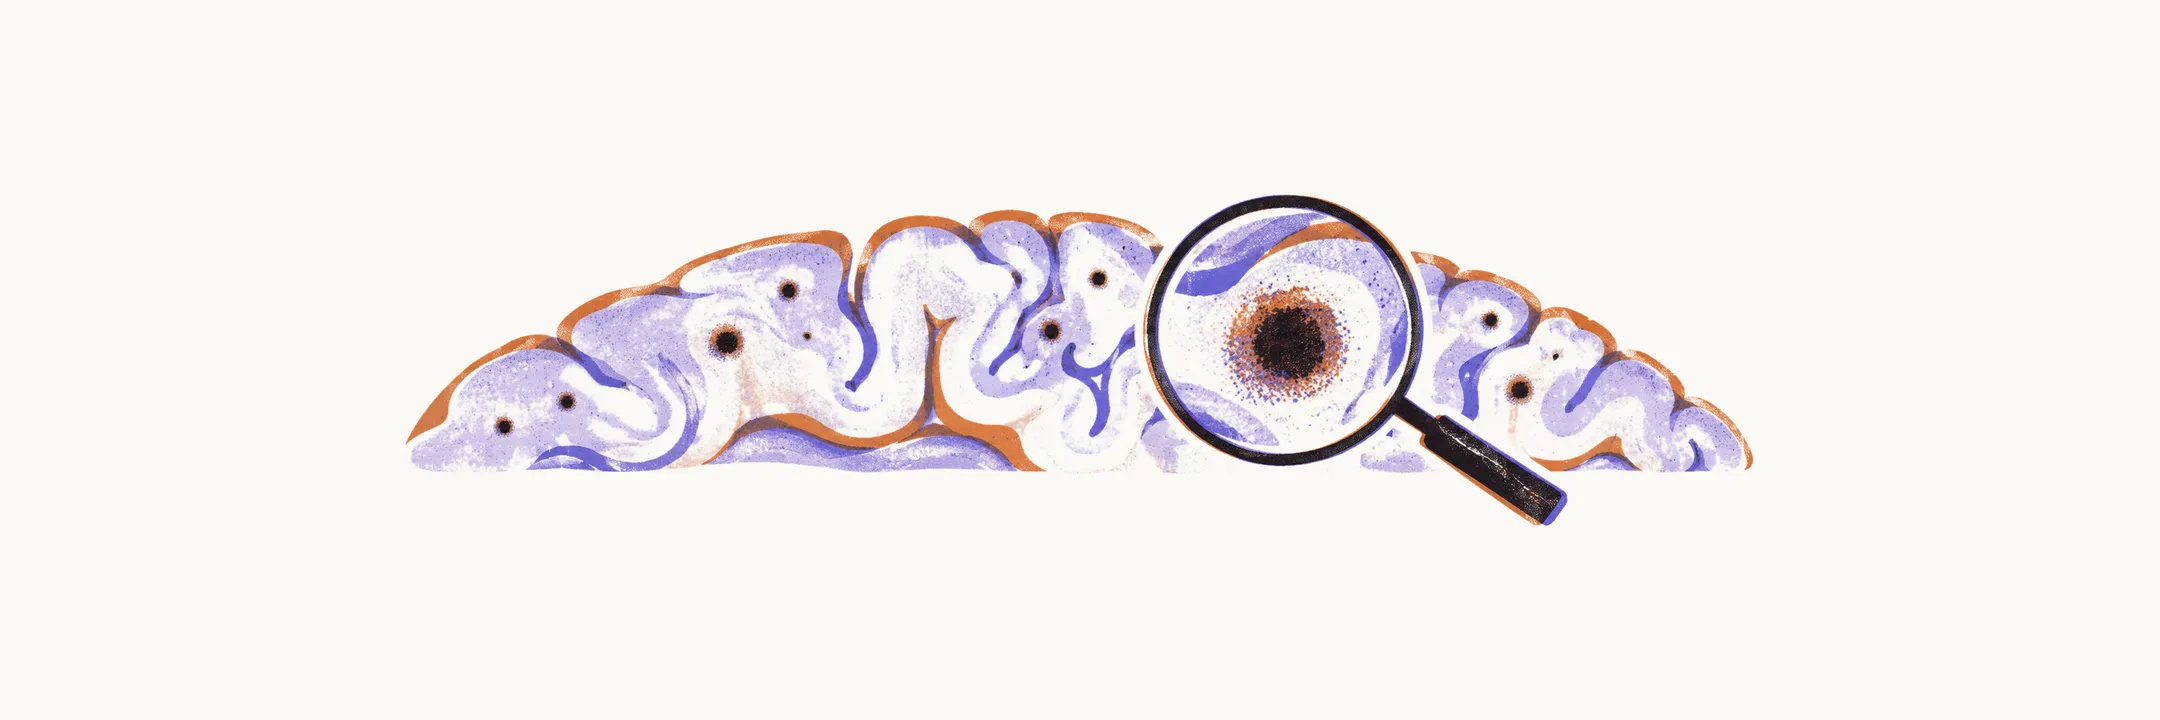
The diagnostic key is blood-sensitive MRI: the gradient-recalled echo (GRE) sequence, also called T2-star, and susceptibility-weighted imaging (SWI). These sequences detect hemosiderin, the iron-containing residue of old blood, from old microbleeds that are invisible on CT and on standard T1, T2, and FLAIR images. Microbleeds appear as small dark foci of signal loss, and their lobar distribution is what points toward amyloid angiopathy rather than hypertensive disease.
Imaging features
Several imaging findings, taken together, build the picture. The haemorrhagic ones carry the most weight: lobar microbleeds distributed across cortical territories, often multiple, and lobar intracerebral haemorrhage, frequently occipital or parietal in acute presentations. Cortical superficial siderosis adds linear hemosiderin along the cortical surface.
Two white matter findings support the diagnosis without proving it on their own: white matter hyperintensities on FLAIR (bright areas of white matter change) and enlarged perivascular spaces in the centrum semiovale (the deep white matter of the cerebral hemispheres).
Boston version 2.0 framework
The Boston criteria grade diagnostic certainty from definite disease (full postmortem examination) through pathology-supported and clinical levels. Version 2.0 applies to patients aged 50 years or older presenting with intracerebral haemorrhage, transient focal episodes, or cognitive impairment, with no deep haemorrhagic lesions and no other cause.
It added two white matter features alongside the haemorrhagic lesions: severely enlarged perivascular spaces in the centrum semiovale and a multispot pattern of subcortical white matter hyperintensities.
In outline, probable disease requires either at least two strictly lobar haemorrhagic lesions (haemorrhage, microbleed, or superficial siderosis) or one such lesion combined with a qualifying white matter feature. Possible disease requires a single strictly lobar haemorrhagic lesion or a single qualifying white matter feature. In practice, a clinical diagnosis of probable disease is sufficient to guide management decisions such as antithrombotic avoidance.
Amyloid angiopathy versus hypertensive bleeding
| Feature | Amyloid angiopathy | Hypertensive small-vessel disease |
|---|---|---|
| Haemorrhage location | Lobar (cortical) | Deep (basal ganglia, thalamus, pons) |
| Typical age | Usually past 70 | Often 50 to 70 |
| Microbleeds on blood-sensitive MRI | Lobar distribution | Deep distribution |
| Management implication | Generally avoid antithrombotics | Blood pressure control central |
The table describes typical patterns rather than absolute rules, and mixed disease occurs: an older hypertensive patient can carry both pathologies, in which case the strictly lobar lesions still argue for coexisting amyloid angiopathy.