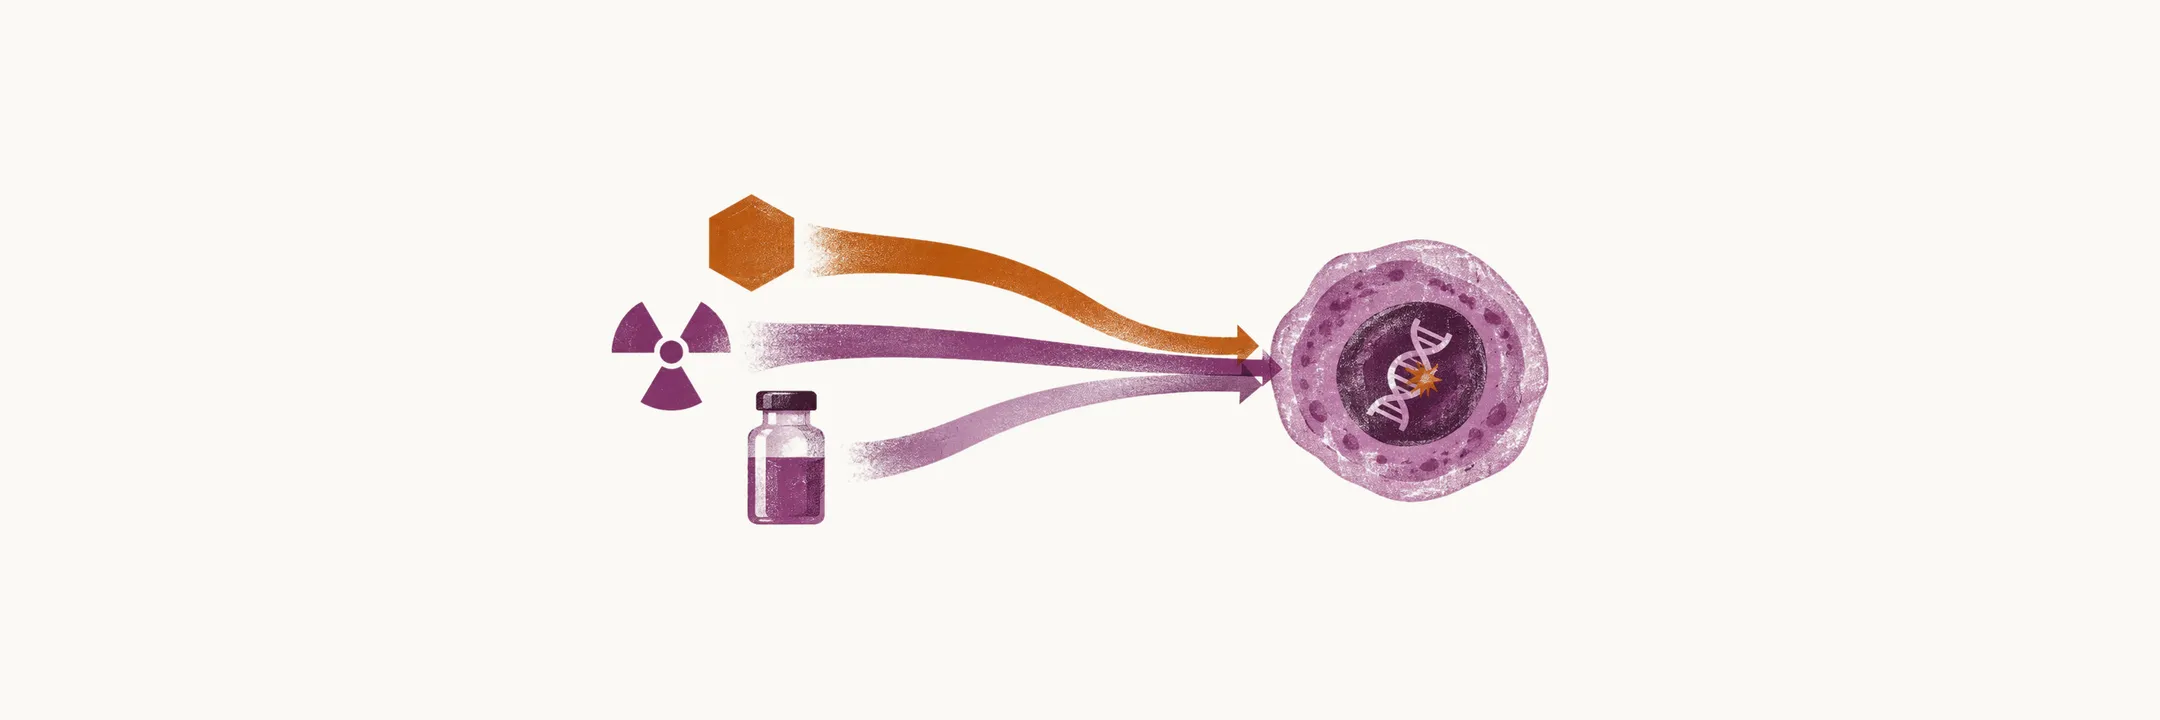
The causes of acute myeloid leukemia are mostly unknown, but several exposures and inherited conditions raise the risk.
Etiology
Most cases of AML are idiopathic or primary, meaning that no specific exposure or inherited condition is identified. In the remaining cases, several factors are implicated, and they all act in the same way: by increasing the chance that a hematopoietic (blood-forming) cell acquires the somatic mutations, which are acquired during life rather than inherited, that lead to leukemia.
Chemical and occupational exposure is one such factor, and benzene is the best-established example; exposure to ionizing radiation is another. Previous cancer treatment is a third: cytotoxic chemotherapy and radiotherapy given for an earlier cancer raise the risk of a later, therapy-related myeloid neoplasm, which typically appears years after the original treatment.
The inherited forms of AML are very rare, but the presence of germline mutations, which are inherited and present in every cell of the body, that predispose an individual to AML has recently been proved. The main germline mutations related to AML are:
- CEBPA
- DDX41
- RUNX1
- GATA2
- ANKRD26
- ETV6
What matters clinically is that AML arising from a germline mutation is mostly part of a well-described syndrome rather than an isolated finding. These syndromes include the bone marrow failure syndromes — Fanconi anemia, Shwachman-Diamond syndrome and Diamond-Blackfan anemia — and the telomere biology disorders such as dyskeratosis congenita. Inherited defective DNA repair can also evolve into AML, as in Fanconi anemia, Bloom syndrome and ataxia-telangiectasia, and congenital neutropenia, called Kostmann syndrome, carries the same risk.
Beside the germline mutations, some somatic genetic abnormalities are important. In Down syndrome, for instance, the presence of a GATA1 mutation makes these patients more prone to the megakaryocytic type of AML, the form arising from the platelet-producing cell line.