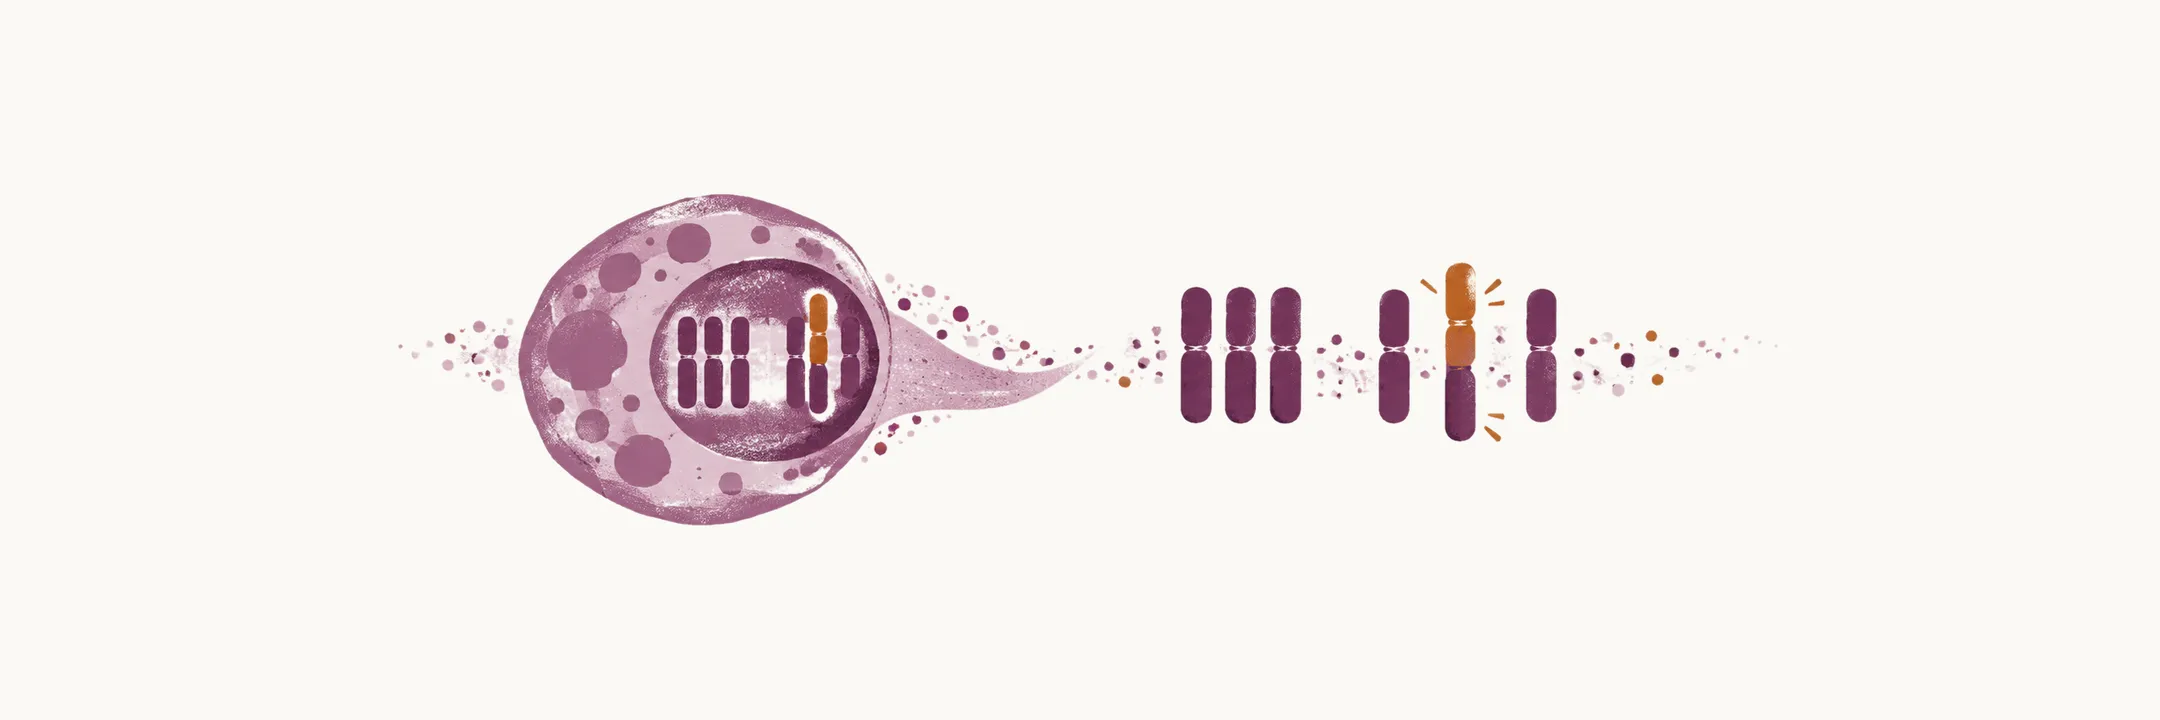
Multiple myeloma, or MM, is a malignant proliferation of plasma cells which are derived from a single clone. A plasma cell is the mature B cell that secretes antibody, so the myeloma cell keeps that job and over-produces a single immunoglobulin, the M protein.
Where the myeloma cell comes from
Plasma cells begin their development in the germinal centre of the lymph nodes, where a B cell that recognises its antigen is selected and reshapes its immunoglobulin, and these cells then transfer to the bone marrow, where they settle as long-lived antibody-producing cells. In a normal healthy person, plasma cells are only a small proportion of the bone marrow cells, normally less than 5%; in the case of MM, plasma cells are present in the bone marrow in increased numbers.
Epidemiology
The incidence of myeloma is increased by age: the median age of diagnosis for MM is about 69 years. It is more frequent in males, and the incidence in Black people is twice the incidence in White people. It is the second most common form of hematological cancer, after non-Hodgkin lymphoma.
The etiology of MM, meaning its cause, is not known yet, but it is more common in farmers, leather workers, workers with petroleum, and people with contact with ionising radiation.
Genetic abnormalities
There is no single exact genetic defect in MM, as can be seen in lymphoma and leukemia. Instead, the malignant clone is built up from a combination of changes, and two broad patterns account for most cases. A trisomy is an extra copy of a chromosome, and a translocation joins a segment of one chromosome to another. A variety of genetic abnormalities can be seen in MM:
- half of the cases are affected by trisomies of chromosomes 3, 5, 7, 9, 11, 15, 19 and 21, which raise the copy number of whole chromosomes, a state called hyperdiploidy
- the other half of cases carry a translocation of the immunoglobulin heavy-chain locus on chromosome 14 — t(11;14), t(4;14) or t(14;16) — which places a growth-controlling gene beside the powerful heavy-chain enhancer and switches it on permanently: t(11;14) drives cyclin D1 (CCND1), t(4;14) drives NSD2 (MMSET) and FGFR3, and t(14;16) drives MAF
- other, less frequent, ones are: 13q14 deletion, 17p13 deletion, 1p deletion and 1q amplification
There is strong evidence behind the idea that errors in switch recombination, the process that changes the isotype of an antibody, participate in the early transformation of MM: the translocations above are placed at exactly the sites where that recombination normally happens.
Genome sequencing was not able to detect a single mutation that is involved in more than 20% of cases of MM, but collectively more than 40% of cases of MM have a mutation in one of the B-raf, N-ras and K-ras genes, all of which sit on the same growth-signalling pathway. The disease is therefore driven by several cooperating lesions rather than by one dominant mutation.
Classification of plasma cell dyscrasias
The latest classification of plasma cell dyscrasias by the WHO, which includes the genetic subtypes above, is:
- non-IgM monoclonal gammopathy of undetermined significance, or MGUS
- multiple myeloma, divided into multiple myeloma NOS (not otherwise specified) and multiple myeloma with recurrent genetic abnormalities — the CCND family translocation (related to chromosome 11), the MAF family translocation (related to chromosome 16), the NSD2 family translocation (related to chromosome 4) and hyperdiploidy
- solitary bone plasmocytoma
- solitary extramedullary plasmocytoma
The classification runs from the premalignant precursor, MGUS, through overt multiple myeloma and its genetic subtypes, to the solitary plasmocytomas, in which the plasma cell tumour is confined to a single site.