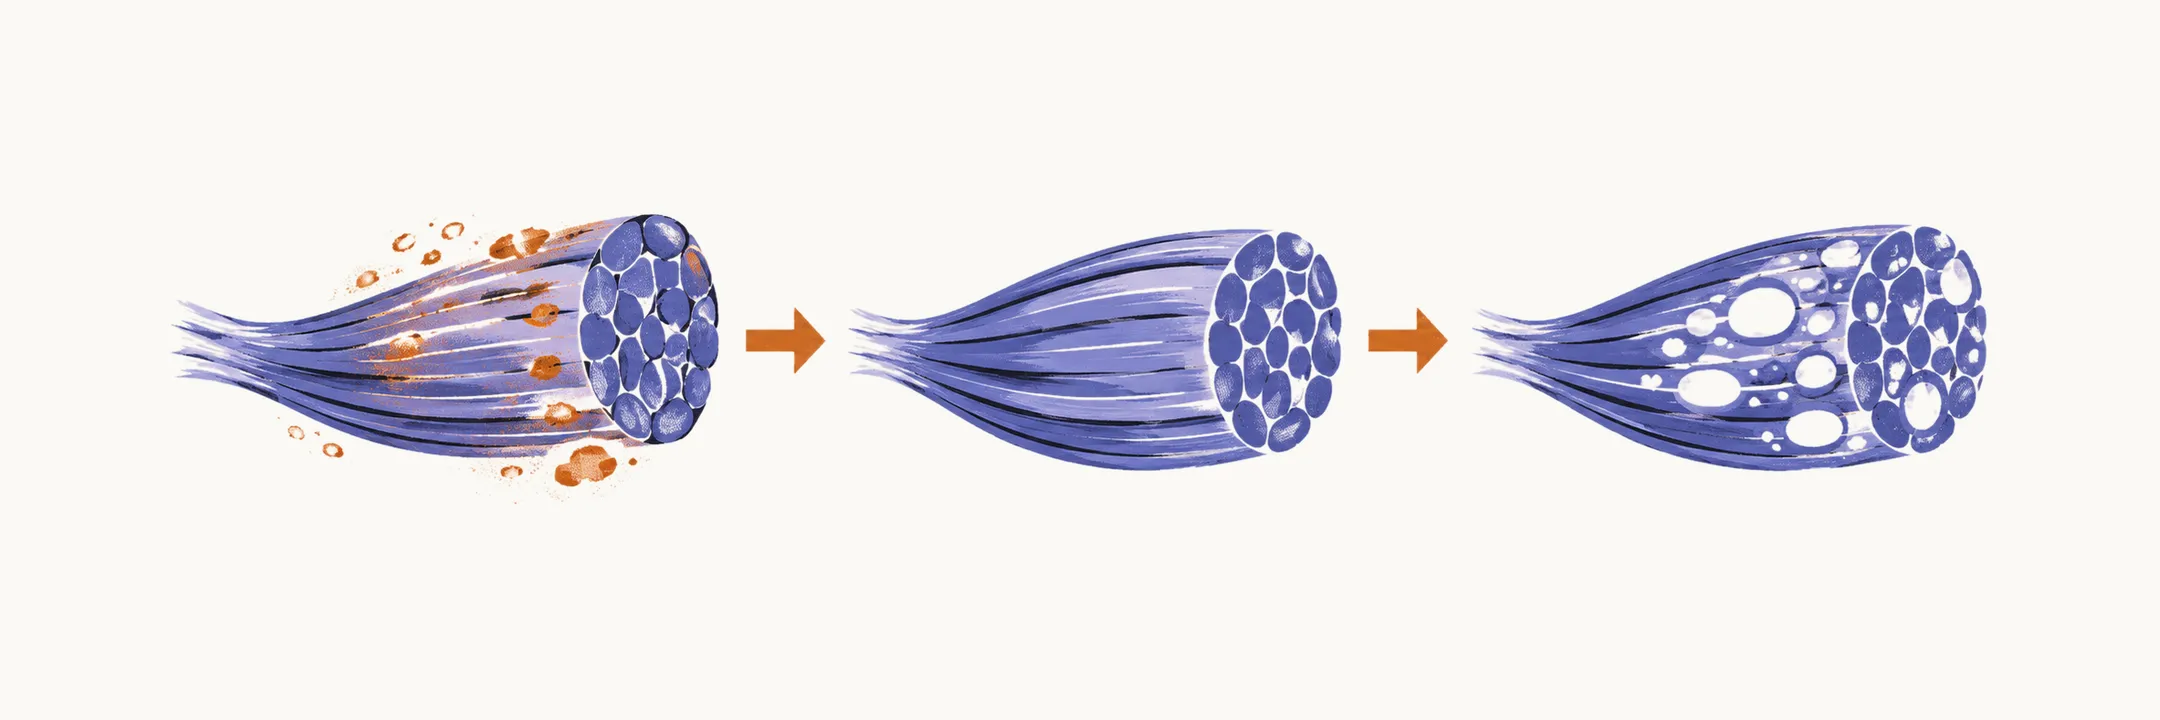
A rash with proximal weakness, weakness of the muscles nearest the trunk, means dermatomyositis until proven otherwise. The work of the differential is to know when that assumption is wrong, because several muscle diseases produce the same pattern of weakness and each one is managed differently. Five features carry most of the separation: the presence of a rash, the distribution of weakness, the age at onset, the level of creatine kinase (CK, an enzyme released from injured muscle fibres), and the response to immunosuppression.
Dermatomyositis and polymyositis
Polymyositis produces the same proximal, symmetric weakness and the same markedly raised creatine kinase, usually in middle adulthood, and it responds to the same treatment. What separates it is what it lacks. There is no rash, the biopsy shows cytotoxic T cells invading fibres within the fascicle rather than perifascicular atrophy, and the diagnosis is one of exclusion, so a rash-free patient needs the other causes of proximal weakness excluded before the label is applied.
Dermatomyositis and inclusion body myositis
Inclusion body myositis begins after the age of 50 and, unlike the other inflammatory myopathies, does not respond to immunotherapy. The distribution is the tell: finger flexor weakness, with difficulty gripping or opening jars, together with quadriceps weakness, with falls and difficulty rising from a chair, and the pattern may be asymmetric. Creatine kinase is normal or only mildly raised, and biopsy shows rimmed vacuoles. Finger flexor weakness in an older patient whose strength is unmoved by steroids means inclusion body myositis, not a reason to escalate immunosuppression.
The three inflammatory myopathies side by side
Set beside one another, the three inflammatory myopathies differ on several features at once.
| Feature | Dermatomyositis | Polymyositis | Inclusion body myositis |
|---|---|---|---|
| Rash | Present in the large majority | Absent | Absent |
| Weakness pattern | Proximal, symmetric, legs more than arms | Proximal, symmetric | Finger flexors plus quadriceps, sometimes asymmetric |
| Onset | Any age, with a childhood peak | Middle adulthood | Over 50 years |
| Sex pattern | Female-predominant | Female-predominant, less marked | Male-predominant |
| CK | Markedly raised in active disease | Markedly raised | Normal or mildly raised |
| Biopsy hallmark | Perifascicular atrophy | Endomysial cytotoxic invasion | Rimmed vacuoles |
| Calcinosis | Common in juvenile disease, rare in adults | None | None |
| Cancer association | Strong in adult onset | Moderate | None |
| Treatment response | Good | Good | None to immunotherapy |
Other causes of proximal weakness
Not every weak patient with a raised or normal creatine kinase has an inflammatory myopathy. Several other conditions produce proximal weakness, each with a feature that separates it:
- Muscular dystrophies progress insidiously over years rather than days to weeks and often carry a family history.
- Endocrine myopathies, such as those of thyroid disease, are painless and improve when the hormone abnormality is corrected.
- Metabolic myopathies produce pain and cramps triggered by exertion rather than fixed weakness.
- Drug-induced myopathy: drugs, including statins and glucocorticoids, can weaken muscle directly, and removing the drug is the test.
- Immune-mediated necrotising myopathy is a further acquired cause, recognised by a very high creatine kinase and by antibodies such as anti-SRP or anti-HMGCR.
A normal or only mildly raised creatine kinase does not exclude an inflammatory myopathy, particularly when the skin is involved and there is little muscle disease.