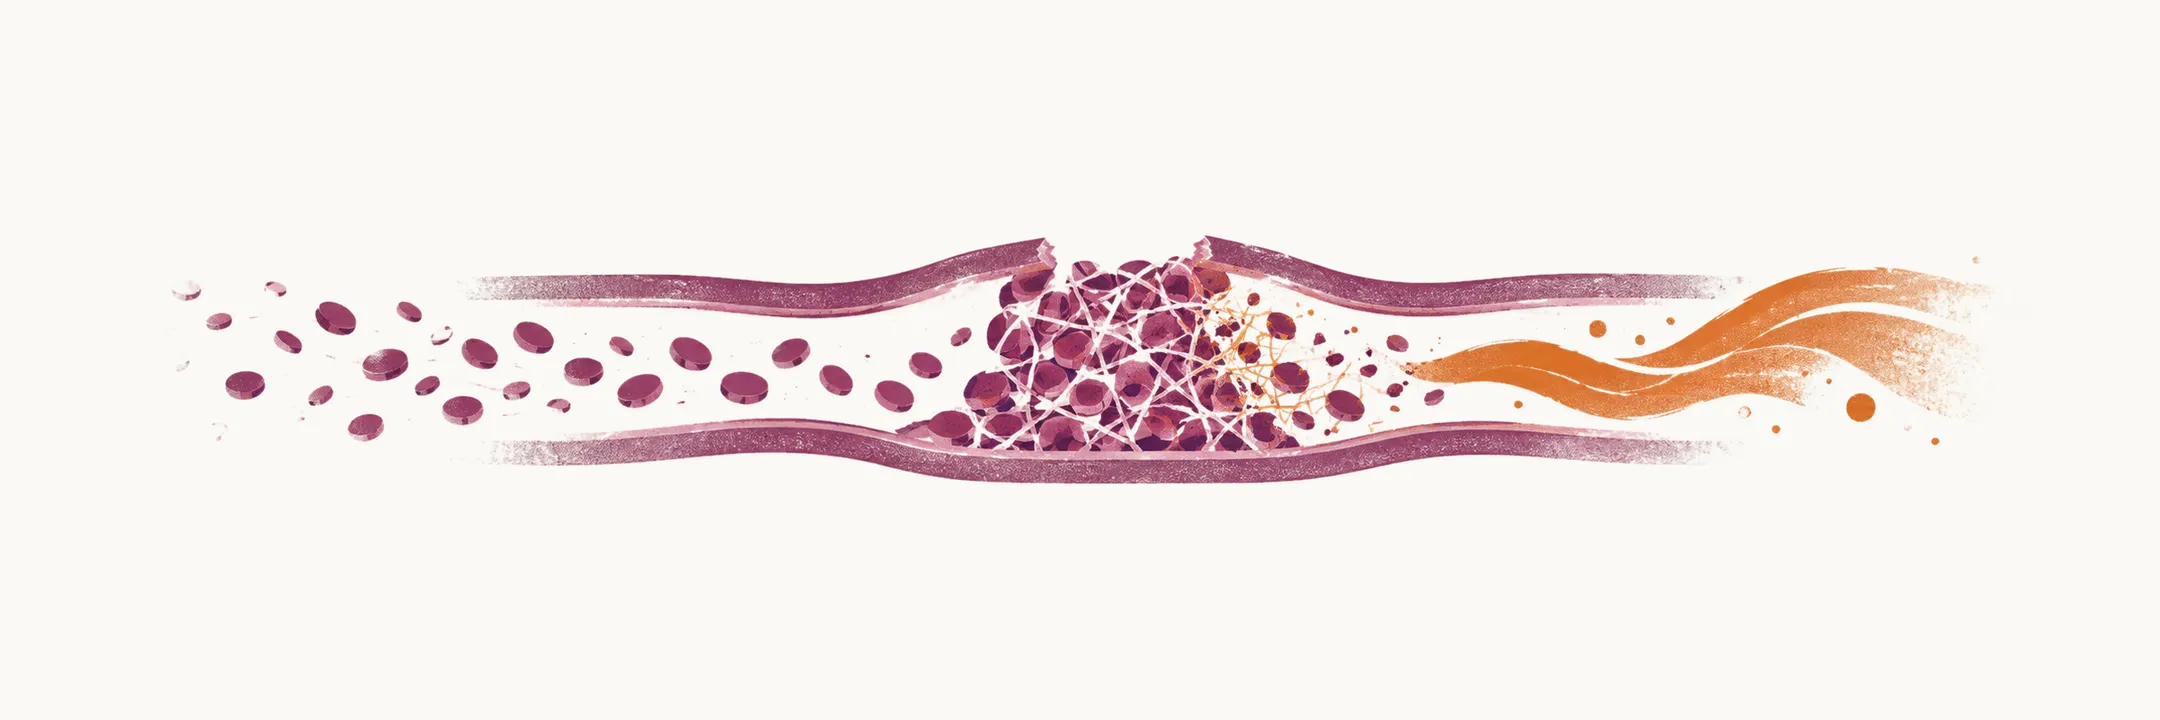
Hemostasis is the set of reactions that seal a damaged vessel with a clot and then remove that clot. In the normal physiological condition, there is a balance between the pro-coagulant forces, which are platelet adhesion and aggregation and fibrin clot formation, and the anti-coagulant forces, which are fibrinolysis and the natural inhibitors of coagulation. Bleeding and thrombosis appear when that balance is disturbed.
The major components of the hemostatic system are platelets, together with other circulating cells such as red cells and monocytes; the plasma proteins of clotting and its inhibitors; and the vessel wall.
Hemostasis is made up of five steps, and the first three build the clot while the last two limit it and remove it:
- endothelial injury and vasoconstriction
- platelet plug formation
- activation of the clotting cascade
- termination of clotting under the control of anti-thrombotic factors
- fibrinolysis
The topic therefore divides into two parts: how hemostasis works, and how a bleeding disorder is recognised and assessed. Readers new to the subject can begin with platelets and read in order.
How hemostasis works
The first four notes follow the five steps, from the cells and proteins that build the clot to the systems that restrain and dissolve it.
- Platelets: What They Are and How They Are Produced explains what platelets are, how the bone marrow makes them, and the basic figures of size, normal count, lifespan and the fraction held in the spleen.
- Coagulation: Primary and Secondary Hemostasis works through platelet plug formation (primary hemostasis) and fibrin clot formation (secondary hemostasis), including the extrinsic and intrinsic pathways and the central role of thrombin.
- Anti-thrombotic Mechanisms covers the endothelial products that limit platelet adhesion and coagulation, and then antithrombin, protein C with its cofactor protein S, and tissue factor pathway inhibitor.
- The Fibrinolytic System explains how plasmin is formed from plasminogen, how it is targeted to fibrin, the inhibitors that control it, and how D-dimers, the fibrin fragments released when a clot is broken down, report that breakdown.
How a bleeding disorder is assessed
The remaining notes follow the clinical sequence: naming the lesions, taking the history, examining the patient, choosing and interpreting laboratory tests, and finally the patient who is bleeding now.
- Bleeding Terminology defines petechiae, purpura, ecchymosis, hematoma and major bleeding, the words that recur throughout the clinical assessment.
- History of Bleeding collects the questions that matter, from past and procedure-related bleeding to spontaneous bleeding, family history, drugs and systemic disease, and what each pattern suggests about the underlying defect.
- Physical Findings in Bleeding Disorders reviews the skin, joint, cardiac and other findings on examination that raise suspicion of a bleeding disorder.
- Laboratory Testing for Bleeding Disorders explains the initial screen of blood count, platelet morphology, prothrombin time (PT) and activated partial thromboplastin time (aPTT), how each coagulation test is performed, and the extra tests used when secondary or primary hemostasis defects are suspected.
- Interpreting Bleeding Disorder Tests sets out the patterns of prolonged PT and aPTT, prolongation of one of them alone, and the disorders to consider when the history is positive but the initial tests are normal.
- Managing the Actively Bleeding Patient covers the search for the bleeding source and the measures that support hemostasis, from platelet transfusion thresholds to fibrinogen, vitamin K, clotting factor concentrates and antifibrinolytic agents.